TL;DR for operators
An upstream lesion mask can be informative without being reliable enough to use as the final answer. The paper behind FreNet asks a more operationally useful question: can that imperfect mask control how the downstream model represents the image?
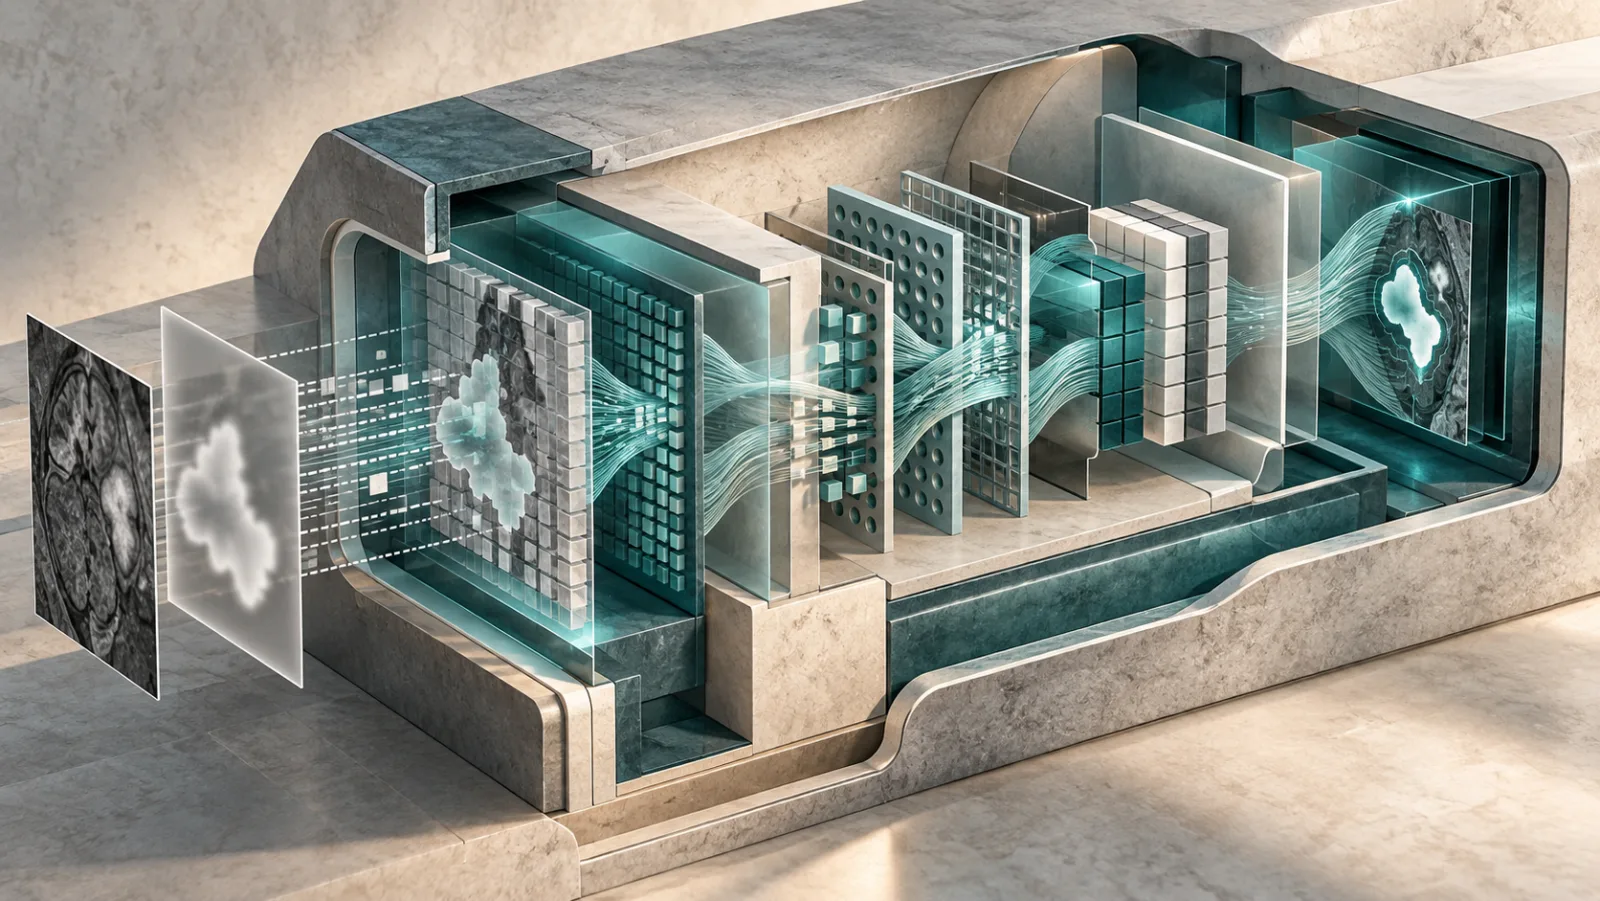
Its answer is a two-stage design. Before normal feature extraction, the mask helps reweight the input at pixel level. During encoding, the system reorganizes intermediate features by frequency and then restores spatial alignment with a refined version of the prior. In the reported ablations, this distinction matters: on ETIS, the PVT baseline achieves 75.0 Dice, and adding SAM guidance alone also produces 75.0; the full configuration reaches 82.0.
For medical-imaging teams, the architectural implication is modular. A general segmentation model can provide guidance while a task-specific model retains control over where, when, and how that guidance influences representation learning. The paper tests this pattern across nine 2D benchmarks and several prior-quality conditions, but it does not establish prospective clinical performance. It also reports higher computational cost, and its own benchmark table contains a notable counterexample: on CVC-300, the SAM-based FreNet variant scores below SAM itself.
An upstream mask does not decide how the image should be represented
Consider a lesion-segmentation pipeline receiving a mask from a capable upstream model. The mask identifies much of the lesion, but it may also activate background tissue, miss weak boundaries, or represent an irregular lesion imperfectly.
Passing that mask downstream does not solve the representation problem. The next model still has to decide which image regions deserve emphasis, which apparent boundaries are noise, and how intermediate features should separate lesion from background.
That distinction is visible in the paper’s ETIS ablation. A PVT-based baseline records 75.0 Dice. Adding SAM guidance without the paper’s two reconfiguration mechanisms leaves Dice at 75.0. Only when the prior begins altering representations through the proposed modules does performance rise: adding the early reconfiguration mechanism lifts Dice to 77.8, while the complete configuration reaches 82.0.
This is the central contribution of Feature Reconfiguration With Visual Prior for Medical Lesion Segmentation.1 FreNet does not use SAM as the segmentation system to be fine-tuned into the final answer. SAM supplies a visual prior to a PVTv2-based pipeline, and that prior is subsequently transformed and reused.
The interesting engineering decision is therefore not simply whether to add a foundation-model mask. It is where that uncertain guidance enters the downstream computation.
IPNN changes the input before the backbone inherits its mistakes
FreNet’s first intervention occurs before normal feature extraction.
Its Implicit Prior Neural Network, or IPNN, combines two kinds of information: each pixel’s normalized spatial coordinates and a representation derived from the SAM mask. From these, it generates location-specific channel weights and applies them through residual gating to the original input.
Conceptually, the mechanism asks: given where this pixel is and what the upstream mask suggests about the image, how strongly should the downstream encoder respond here?
The residual form matters. FreNet is not replacing the image with the prior or zeroing everything outside a predicted lesion. It retains the original representation while adding prior-conditioned modulation. That gives the model a path to preserve image information even when the upstream mask is incomplete.
The paper’s Grad-CAM analysis is consistent with the intended mechanism: after IPNN, activation becomes more concentrated in lesion regions while background activation is reduced. This is mechanism-supporting evidence rather than clinical validation, but it helps explain why merely possessing the same SAM mask is not equivalent to using it before encoding.
For a product architecture, the distinction is consequential. Upstream guidance becomes an input to representation control rather than an output that the downstream component must simply accept.
DFR separates frequency information, then restores spatial meaning
Early reconfiguration does not finish the job. Lesions vary in size, texture, edge definition, and morphology, so FreNet intervenes again between backbone stages with its Dual-domain Feature Reconfiguration module.
The first component, the Frequency Decoupling Module, applies a 2D Fourier transform and partitions the representation into four frequency bands. Those bands are individually refined and then recombined with trainable weights. The paper’s internal comparison reports that its ratio-based frequency partitioning performs better than the linear and logarithmic alternatives it tests.
Frequency separation, however, introduces its own problem: a representation can become better organized by frequency while losing the spatial coherence needed for segmentation.
FreNet therefore follows frequency processing with a Spatial Localization Module. It first refines the prior by blending the original mask with low- and high-frequency responses. It then calculates point-wise similarity between the frequency-optimized representation and that refined prior. Similarity-aligned features are emphasized, complementary positive responses are retained, and the original backbone feature is added back through a residual path.
The two components address different failure modes. Frequency decoupling attempts to improve lesion-background discrimination; spatial localization reconnects those transformed features to where the lesion is likely to be.
The internal DFR ablations support that pairing. Removing either the frequency component or the spatial component reduces Dice and mIoU relative to the complete configuration on ISIC2018, BUSI, and ETIS. This is an ablation result—not a second independent benchmark claim—but it supports the authors’ decision to treat frequency restructuring and spatial recovery as complementary operations.
The strongest evidence is architectural, not just a higher benchmark score
FreNet is evaluated on nine 2D datasets spanning dermoscopy, ultrasound, and endoscopy. Across those benchmarks, the reported results are generally higher than the compared methods on Dice and mIoU.
ETIS provides the most pronounced example highlighted by the paper. The SAM-based FreNet configuration reaches 82.0 Dice and 74.1 mIoU, versus 74.8 and 68.4 for SAM. Relative to the strongest other result reported in the table, the Dice improvement is 5.0 percentage points.
But the ablation structure is more informative than that headline number because it tests the paper’s architectural claim directly.
| Configuration on ETIS | Dice | mIoU | What the comparison tests |
|---|---|---|---|
| PVT baseline | 75.0 | 66.2 | Task-specific backbone without prior guidance |
| + SAM | 75.0 | 68.0 | Presence of upstream guidance alone |
| + SAM + IPNN | 77.8 | 69.9 | Early prior-conditioned input reconfiguration |
| + SAM + DFR | 80.0 | 72.3 | Intermediate dual-domain reconfiguration |
| + SAM + IPNN + DFR | 82.0 | 74.1 | Combined staged reconfiguration |
The pattern does not show that every component will produce the same increments elsewhere. It does show why describing FreNet as “SAM plus another segmentation network” misses the mechanism being tested. On ETIS, access to the prior alone does not generate the main Dice gain; changing how that prior affects representations does.
Imperfect priors are part of the design problem
A production system cannot assume that an upstream mask will always be high quality. FreNet explicitly analyzes low-, medium-, and high-quality SAM masks and reports gains across all three groups. The paper highlights a 33.0% performance gain for the low-quality ETIS group.
This analysis is best read as a robustness test. It supports the narrower proposition that FreNet can still extract value from varying prior quality within the tested setting. It does not demonstrate robustness to every type of upstream failure, scanner shift, patient population, or deployment condition.
The authors also replace SAM with TransUNet as the prior-producing network. The resulting configuration improves on most reported datasets, suggesting that the architecture is not intrinsically tied to one foundation model.
That is particularly relevant to system design. The reusable idea may be the interface between an upstream prior generator and a downstream task model: the prior can be swapped, while the downstream system retains mechanisms for gating, refining, and localizing its influence.
The benchmark also shows where the story stops
The results are broad, but they are not uniformly positive. On CVC-300, the SAM-based FreNet variant reports 86.7 Dice and 79.3 mIoU, below SAM’s 87.8 and 81.5. That table entry conflicts with the paper’s broader prose claim of improvement over SAM across all nine datasets.
For operators, that exception is useful. It prevents the architecture from being interpreted as a rule that prior reconfiguration must dominate direct foundation-model output on every dataset.
There is also a deployment cost. The authors identify increased computational cost as FreNet’s main limitation. The full model contains 38.31 million trainable parameters, compared with 25.4 million attributed to the backbone; IPNN itself is small at 0.04 million parameters, while DFR contributes 2.97 million. The authors propose knowledge distillation as future work.
More importantly, all reported validation is retrospective and benchmark-based. The nine datasets provide meaningful cross-modality evidence for the architecture, but they do not establish prospective clinical safety, workflow performance, calibration under real hospital conditions, or deployment readiness.
Treat foundation-model output as governed guidance
Cognaptus’ inference from this paper is broader than lesion segmentation but narrower than a claim about clinical AI generally.
When an upstream foundation model produces an informative but imperfect intermediate output, a downstream specialist model may benefit from controlling how that output alters representation learning rather than treating it as a final answer or a passive extra input.
FreNet implements that principle at two points: before encoding, where the prior changes pixel-level emphasis, and during encoding, where the model restructures frequency information and restores spatial localization. Its benchmark and ablation evidence suggest that this staged use of the prior can matter more than simply making the prior available.
For medical-imaging product teams deciding how to combine general models with task-specific components, that shifts the architecture question. The interface between models is not merely a data pipe. It can be an explicit control layer that decides when uncertain upstream information is amplified, revised, or bypassed.
FreNet provides a concrete implementation of that idea. The next test is whether the same control survives the conditions the benchmark does not cover: prospective clinical workflows, distribution shift, latency constraints, and failure modes in which the upstream prior is systematically wrong rather than merely imperfect.
Cognaptus: Automate the Present, Incubate the Future.
-
Yinan Liu and Jiankang Hong and Zhen Gao and Ye Lu (2026). Feature Reconfiguration With Visual Prior for Medical Lesion Segmentation. arXiv:2609.03535. https://arxiv.org/abs/2609.03535 ↩︎